
MPH Part 4: Preparations, Miscellaneous
15. Long-term effects: No tolerance effects with MPH
A study of people with ADHD who took MPH for 2 years showed a significant worsening of hyperactivity and inattention upon discontinuation of MPH, which corresponds to a recurrence of the symptoms that had been improved by MPH.1
A placebo-controlled withdrawal trial involving people with ADHD who had taken MPH for over 2 years showed that discontinuing MPH caused a significant increase in ADHD symptoms.2 Nevertheless, for some people with ADHD, continued medication appears to be unnecessary after a certain period of time, which justifies conducting regular withdrawal trials.
A meta-analysis of 87 randomized, placebo-controlled, double-blind studies found no evidence of a decline in the efficacy of methylphenidate, amphetamine-based medications, atomoxetine, or α2-antagonists with long-term use.3
A meta-analysis found only one RCT that compared the effects of a single dose of MPH with those of longer-term use (in this case, 4 weeks). This RCT found a significant consistency between the effects of a single dose and those of prolonged use. This is relevant for the evaluation of studies on the effects of single doses of MPH.4
16. Gender Differences in MPH
A study found a greater increase in dopamine levels in the ventral striatum (including the nucleus accumbens) in women than in men. The increase in the dorsal striatum was the same.5
17. Indications for Methylphenidate Compared to Other ADHD Medications
- According to the current European consensus, methylphenidate is the first-line choice of medication for ADHD in children (ahead of amphetamine-based medications) and the second-line choice of medication for adults (after amphetamine-based medications)67
- For children who are MPH non-responders—that is, who do not respond to MPH—the effectiveness of amphetamine medications should be evaluated.
- People with severe dysphoria when inactive or with comorbid depression benefit particularly from amphetamine medications.
- In addition, people with ADHD who need a greater boost of energy may find that amphetamine-based medications work better for them.
- Gifted individuals are said to respond better to amphetamine-based medications than to MPH.8
18. Methylphenidate for Other Disorders
MPH has proven to be helpful in treating attention problems in children with brain injuries (brain trauma).9
Furthermore, MPH is used successfully to treat narcolepsy. In 2007, Ritalin® was the only MPH-containing medication approved for the treatment of narcolepsy.10
In children with ASD, MPH appears—unlike in ADHD—to also increase cognitive processing speed.11
19. Taking Methylphenidate Abroad
For more details on this, see the article Taking Stimulants Abroad
20. MPH medication significantly reduces the risk of addiction
The updated 2018 European Consensus on the Diagnosis and Treatment of ADHD concludes that stimulants significantly reduce the risk of addiction while they are being taken.12
People with ADHD and comorbid cocaine addiction showed a significant reduction in addictive behavior when treated with stimulants. This reduction corresponded to the decrease in ADHD symptoms.13
The international consensus on screening, diagnosis, and treatment of adults with addiction and ADHD recommends treatment with long-acting stimulants, starting with low doses and gradually increasing to high doses, in combination with psychotherapy.14
A meta-analysis of 6 studies involving n = 1,014 participants found that participants treated with stimulants (in this case, MPH) had a significantly reduced risk of developing addiction later in life.15 According to the findings, the risk of later addiction—whether to alcohol or other substances—is 1.9 times lower, meaning it is nearly halved.16
A Swedish cohort study found that 3 years after the prescription of stimulants for ADHD, the risk of receiving a diagnosis of addiction was reduced by 31%.17
These findings may be supported by the observation that adolescents with pronounced novelty-seeking tendencies—who, at age 14, exhibited reduced BOLD activity in mesolimbic (nucleus accumbens [ventral striatum] and midbrain) and prefrontal cortical (dlPFC) regions during reward anticipation were more likely to develop problematic drug use by age 16.18 This could be interpreted to mean that ADHD medications that increase dopamine and norepinephrine levels—such as MPH or amphetamine-based medications—directly contribute to reducing the risk of addiction.
ADHD medication reduced the influence of a preference for short-term rewards and frustration intolerance on Internet addiction.19
A study found no increased susceptibility to addiction in adult rodents following treatment with MPH during adolescence.20 Other studies have also found evidence that stimulants do not increase the risk of addiction.21
We believe that the relative importance of the two components—ADHD and addiction—can vary greatly from person to person, and that the success of medication-based treatment depends heavily on this variation. It is therefore likely to depend significantly on the setting in which medication is administered and whether or not it is supported by other measures and intensive support. The practical experience of one of our advisory board members is that treatment focused solely on the substance, without intensive, supporting co-treatment, usually leads only to the use of an additional substance.
In addition, when addiction and ADHD co-occur, other comorbidities such as depression, etc., are often present, which further complicates treatment, since antidepressants often cease to be effective in cases of substance abuse. Therefore, we believe it is important for the success of treatment that, in cases of co-occurring addiction and ADHD, the process of adjusting medication be initiated following inpatient detoxification and drug abstinence.
“Medication treatment for patients with ADHD who also have substance abuse or substance dependence should be provided by a specialist with expertise in the treatment of ADHD and addiction.”22
Finally, it should be noted that people with ADHD often have difficulty taking their prescribed stimulants regularly and on time. If stimulants were to trigger addictive behavior, this would not be the case. Furthermore, people with ADHD by no means wake up in the morning with a “craving” for their medication. However, no such cases have been reported.
The rumors that ADHD medications cause addictive behavior are simply the consequences of a lack of understanding of the differences between drugs and medications. Doctors who spread such misconceptions harm their patients and risk medical malpractice lawsuits if such advice—which violates clinical guidelines—results in harm.
In our view, one neurophysiological explanation for the reduction in addiction risk associated with MPH could be that MPH increases dopamine levels, whereas dopamine deficiency is associated with increased expression of the CB1 cannabinoid receptor.2324 25 However, in our view, this is contradicted by the fact that there is no known increased risk of THC addiction in Parkinson’s disease.
21. Methylphenidate preparations
There are a large number of methylphenidate medications.
Although they all contain the same active ingredient, people with ADHD respond to them differently. “Individually” means that some people tolerate Product A very well and find it effective, while Product B barely has an effect and causes unpleasant side effects; for others, the effect is exactly the opposite.26
For MPH, sustained-release formulations differ primarily in the proportion of the dose that is released immediately. For U.S. formulations, this proportion is 15, 20, 22, 25, 30, or 37%. One formulation releases 50% immediately and has a distinct double-peaked profile. This results in different onset times and courses of action even with the same daily dose. With the methylphenidate patch, levels of the active d-isomer become measurable only after a delay of about two hours and then rise continuously over the recommended wear time of nine hours. The concentration of the inactive l-isomer reaches 40 to 50% of that of the d-isomer, compared to 1 to 2% with oral administration. More than half of the active ingredient remains in the removed patch. (Review article, E 4)27
A sound MPH treatment regimen should therefore always include taking different formulations, even if one formulation is already effective and has no unpleasant side effects. This is because the only way to determine whether another formulation might be significantly more effective is to test it.
Depending on the specific product, consuming a high-fat meal before or while taking the medication may delay or accelerate the onset of maximum effect and may reduce or increase the intensity of the effect.26 We do not have any specific data on this for the products available in Europe.
21.1. Immediate release formulations
- In general:
- Onset of action after 10 to 20 minutes28
- Peak effect after 60 minutes
- Delayed onset of maximum effect when taken with a high-fat meal26
- Duration of effect: 2.5 to 4 hours
- If taken twice, the maximum dose for the second dose is higher than that for the first dose29
- Average half-life of 2.9 hours (2 to 4 hours)26
Products in the U.S. (as of 2021):
-
Focalin®
- Dexmethylphenidate (hydrochloride)
- Tablet
- 3 to 5 hours
- 2.5 mg, 5 mg, 10 mg
-
Methylin® Oral Solution
- Methylphenidate (hydrochloride)
- Liquid
- 3 to 5 hours
- 5 mg/5 mL, 10 mg/5 mL
-
Ritalin®
- Methylphenidate (hydrochloride)
- Tablet
- 3 to 5 hours (in practice, usually more like 2.5 to 3.5)
- 5 mg, 10 mg, 20 mg
-
various generic drugs
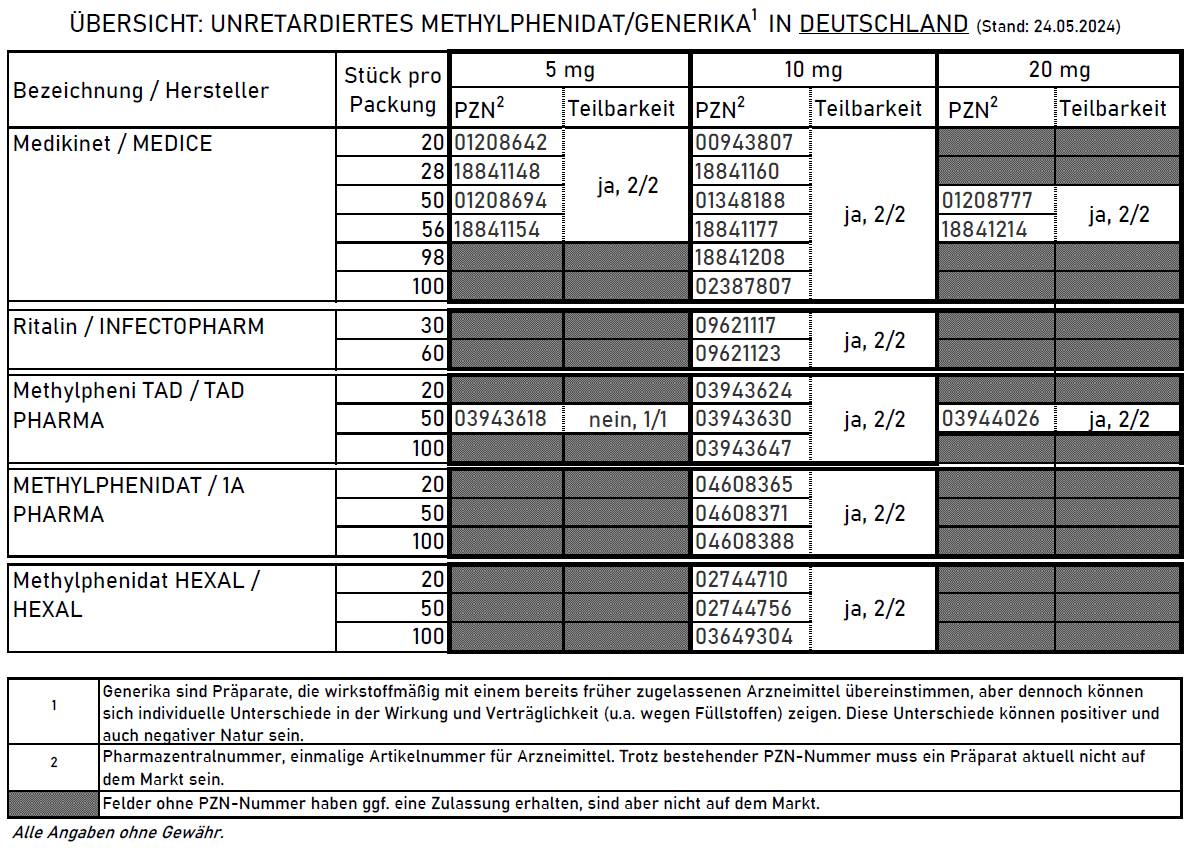
Immediate release formulations in Germany:
- Ritalin® (immediate release)
- 1–3 hours of action time
- Carrier substance: wheat starch30
- Methylphenidate HEXAL®
- 1–3 hours of action time
- Methylpheni TAD® (immediate release)
- 1–3 hours of action time
- People with ADHD reported that the tablets were harder to split than, for example, those from 1A
- Medikinet® immediate release
- 1–3 hours of action time
- Carrier substance: cornstarch30
- various generic drugs
One (and only) pharmacy in Switzerland manufactures MPH drops. These are even easier to dose, making it possible to adjust the dosage precisely even for people with ADHD who require very low doses, such as young children. Ryffel reports on one such application.3132
Graphic: Brainbuzz. Thanks!
21.2. Sustained-release formulations
21.2.1. Half-day dosage
21.2.1.1. Two-phase sustained-release / Extended-release (XR) / Long-acting (LA)
Products in the U.S. (as of 2021):
- Metadate CD® (identical to Equasym XL, EU)
- Methylphenidate (hydrochloride)
- extended-release
- Capsule
- 8 hours
- 10 mg, 20 mg, 30 mg, 50 mg
- Metadate® ER
- Methylphenidate (hydrochloride)
- extended-release
- Tablet
- 8 to 12 hours
- 20 mg
- Methylin® ER
- Methylphenidate (hydrochloride)
- extended-release
- Tablet
- 8 hours
- 10 mg, 20 mg
- QuilliChew ER™
- Methylphenidate (hydrochloride)
- extended-release
- Chewable tablet
- 8 to 12 hours
- 20 mg, 30 mg, 40 mg
- Quillivant XR®
- Methylphenidate (hydrochloride)
- extended-release
- Liquid
- 8, 10, and 12 hours
- 25 mg / 5 ml (5 mg/ml)
- Ritalin LA®
- Methylphenidate (hydrochloride)
- extended-release
- Capsule
- 8 hours
- 10 mg, 20 mg, 30 mg, 40 mg
Half-day-release formulations in Germany:
- Equasym Retard/XL®
- Medikinet Adult®
- Medikinet Retard®
- must be taken with food
- Bioequivalent to Medikinet Adult34
- gluten-free
- contains lactose
- Time until onset of effect: 30 minutes28
- Duration: 6 (up to 8) hours2829
- Efficacy profile:29
- Maximum after 2.5 hours
- then a decline lasting up to 4 hours
- Plateau from hour 4 to hour 6 (lower than the maximum)
- then waste toward the end
- Must be taken before or with a meal28
- The capsule may be opened28
- Contraindicated when taken concurrently with proton pump inhibitors35 - In that case, use Ritalin, for example
- Ritalin LA®
- Bioequivalent to Ritalin Adult
- Duration of effect: 8 hours28 / 6–8 hours26
- Efficacy profile:29
- proprietary sustained-release system SODAS (Spheroidal Oral Drug Absorption System)29
- No food is required before or while taking this medication28
- Delayed onset of maximum effect when taken with a high-fat meal26
- The capsule may be opened and sprinkled on food2926
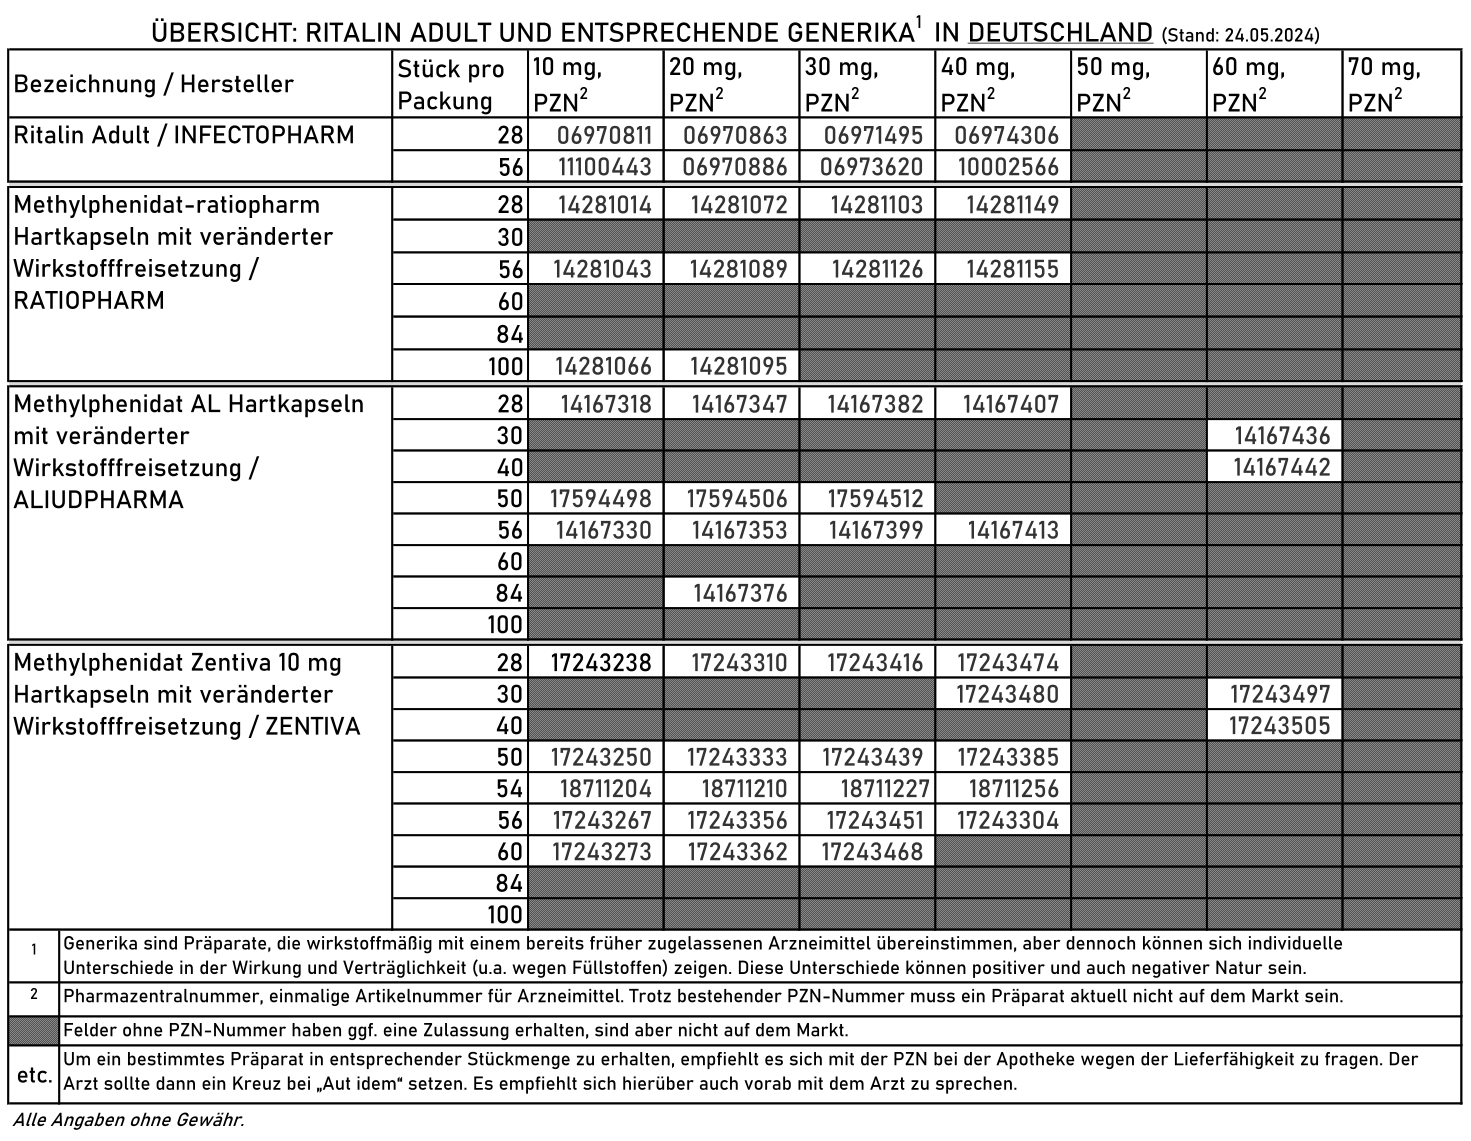
- Ritalin Adult®
- Methysym®
- in Germany since June 1, 2021
- 30% immediate-release, 70% extended-release
- 10, 20, 30, 40, 50, 60 mg
- Up to 8 hours of active time
- No food is required before taking this medication
- Tuzulby (Neuraxpharm)
- for the treatment of ADHD in children and adolescents (ages 6–17)
- Active ingredient: methylphenidate hydrochloride
- sustained release
- 30% immediate-release, 70% delayed-release
- Up to 8 hours of active time
- Cherry-flavored chewable tablet for flexible use without water
- Can also be split; score line at 20 mg/30 mg
- Dosage: The starting dose is usually 20 mg once daily in the morning, and can be adjusted individually in increments of 10, 15, or 20 mg.
- Contains aspartame (E 951)
Graphic: Brainbuzz. Thanks!
| Formulation | ; Release mechanism | ; Immediate release portion | ; Sustained release portion |
|---|---|---|---|
| Concerta | OROS (osmotic system) | 22% | 78% |
| Metadate CD / Equasym XL | Diffucaps | 30% | 70% |
| Ritalin LA | SODAS | 50% | 50% |
| Medikinet retard | enteric-coated pellets | 50% | 50% |
| Aptensio XR / Biphentin | Multilayer-Release | 40% | 60% |
Source: Yang et al. (2016):36
21.2.1.2. Sustained-release
- Ritalin SR®
21.2.2. All-day delay
Products from the U.S.:
Full-day sustained-release formulations (U.S.):
-
Adhansia XR™
- Methylphenidate (hydrochloride)
- extended-release
- Capsule
- 16 hours
- 25 mg, 35 mg, 45 mg, 55 mg, 70 mg, 85 mg
-
- A mixture of
- 70% Serdex methylphenidate (SDX, a prodrug of dexmethylphenidate) and
- 30% dexmethylphenidate (d-MPH) with immediate-release (IR) formulation
- 26.1 / 5.2 mg; 39.2 / 7.8 mg; 52.3 / 10.4 mg SDX/d-MPH
- 13 hours of active time
- Enrollment 2021
- No food is required when taking this medication, but eating does prolong its effect
- Degradation of SDX: unknown enzymes
- Degradation of d-MPH by CES1
- No interaction with CYP2D6, CYP1A2, CYP2C8, CYP2C9, CYP2C19, CYP2E1, or CYP3A
- No interaction with alcohol
- SDX does not prolong the QT interval to a clinically significant degree
- A mixture of
-
Aptensio XR™
- Methylphenidate (hydrochloride)
- extended-release
- Capsule
- 12 hours
- 10 mg, 15 mg, 20 mg, 30 mg, 40 mg, 50 mg, 60 mg
-
Concerta®
- Methylphenidate (hydrochloride)
- extended-release
- Tablet (OROS)
- 10 to 12 hours
- 18 mg, 27 mg, 36 mg, 54 mg, 72 mg
-
Cotempla™XRODT
- Methylphenidate
- extended-release
- Orally disintegrating tablet
- 8 to 12 hours
- 8.6 mg, 17.3 mg, 25.9 mg
-
Daytrana®
-
Methylphenidate
-
Transdermal patch
-
Time until the effect sets in: approx. hours
-
10 to 16 hours
-
10 mg / 9 h (1.1 mg/h)
-
15 mg / 9 h (1.6 mg/h)
-
20 mg / 9 h (2.2 mg/h)
-
30 mg / 9 h (3.3 mg/h)
-
-
Focalin XR®
- Dexmethylphenidate (hydrochloride)
- extended-release
- Capsule
- 12 hours
- 5 mg, 10 mg, 15 mg, 20 mg, 25 mg, 30 mg, 35 mg, 40 mg
-
Jornay PM™
- Methylphenidate (hydrochloride)
- extended-release
- Capsule
- 12+ hours
- 20 mg, 40 mg, 60 mg, 80 mg, 100 mg
Full-day sustained-release formulations in Germany, Austria, and Switzerland:
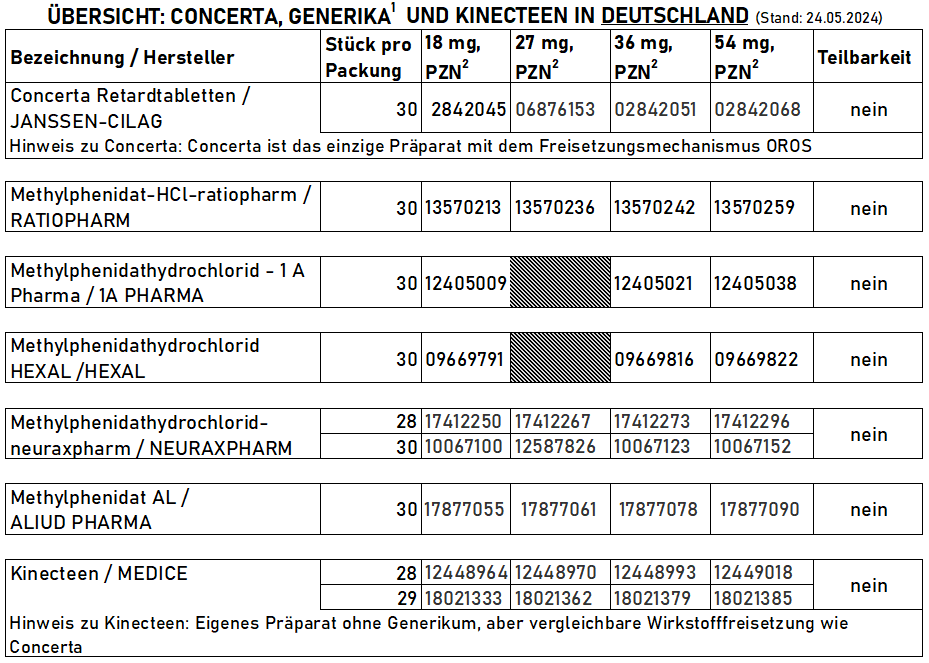
- Concerta®
- Methylphenidate hydrochloride
- extended-release tablets
- 18, 27, 36, 54 mg
- Due to the capsule’s design, a residue of the active ingredient remains in the capsule and is not absorbed
- Therefore, 18 mg corresponds to an intake of approximately 15 mg (27 mg = approximately 22.5 mg, 36 mg = approximately 30 mg, 54 mg = approximately 45 mg)
- Bioequivalent: Methylphenidate Hydrochloride - Neuraxpharm
- Time until onset of effect: 60 minutes28
- Therefore, it is often effective when taken concurrently with a small dose of immediate release MPH
- Taking the medication with or after a meal may delay the time to peak concentration (Tmax) by up to 1 hour and reduce the peak serum concentration (Cmax) by 10 to 30 percent.26
- Duration of effect: 8 to 12 hours;28 10 to 12 hours2629
- Efficacy profile:
- Dosage:
- Methylphenidate Hydrochloride - Neuraxpharm
- 12 hours of effectiveness
- Bioequivalent to Concerta
- No food is required before or while taking this medication
- Kinecteen® (Germany, Austria, Switzerland), Rubicrono® (Spain), Xaggitin® (United Kingdom)
- 12 hours of effectiveness (according to the manufacturer)
- No food is required before or while taking this medication
- Must not be split, chewed, or crushed (as this would negate the sustained-release effect)
- Methylphenidate Hydrochloride Ratiopharm39
- 12 hours of effectiveness
- Methylphenidate Hydrochloride Hexal40
- 12 hours of effectiveness
Graphic: Brainbuzz. Thanks!
The course of the response curve varies considerably depending on the MPH formulation.
22. Drug Concentration-Time Curves for Various MPH Formulations
The time-dependent changes in drug concentrations of various MPH formulations can be plotted on pharmacokinetic curves and compared.4142
A graph illustrates the changes in drug concentration over time for:43
- Concerta
- Ritalin Adult / LA
- Medikinet for Adults
- MPH (immediate release)
A graph illustrates the different drug concentration profiles of Equasym with and without food.44
The Ratiopharm Prescribing Information compares the pharmacokinetic profile of Methylphenidate-Ratiopharm 40 mg with that of Ritalin LA.45
This shows that even bioequivalent formulations do not have completely identical drug concentration-time curves.
The Novartis prescribing information compares the plasma concentration profile of Ritalin LA 40 mg with that of immediate release Ritalin taken twice daily.46
23. Cheating by High School and College Students During Exam Periods
See the section on Misuse of Prescribed Stimulants in the article “ : Stimulants (MPH, AMP) for ADHD”
24. Medications with the Same Active Ingredient, Pharmacies, and Discount Agreements in Germany
Even at the same dose, individual medications often differ in terms of bioavailability, efficacy, duration of action, and side effects.
It often takes some time to find the right medication for each individual and the correct dosage for the patient. If a medication is substituted due to a discount agreement, this can have significant consequences for treatment, including discontinuation of therapy.
Given this context, it is imperative that stimulants be added to the list of substances excluded from substitution therapy.
25. Methylphenidate and Drug Screenings
Medications containing methylphenidate can lead to false-positive laboratory test results for amphetamines, particularly when using immunoassay methods.47
26. Different MPH medications have varying effects on different people—even though they contain the same active ingredient
Although not yet scientifically substantiated, it is empirically and indisputably recognized that methylphenidate preparations can have very different effects on different individuals.48 We suspect this is related to differences in the drug’s efficacy and duration profiles, as well as variations in excipients.
We know people with ADHD who reacted with aggression to one MPH medication but responded exceptionally well to another—and other people with ADHD who had exactly the opposite reactions to the two medications.
This phenomenon is widely known among people with ADHD in forums, and they regularly recommend trying different MPH medications to one another.
Among adults, however, methylphenidate has been increasingly replaced by Vyvanse since Vyvanse Adult was approved in May 2019. For adults, amphetamine-based medications are the first-line choice of medication over methylphenidate.
27. Additional Sources on Methylphenidate
A detailed, illustrated explanation of the mechanism of action of methylphenidate can be found at www.pharmgkb.org.49 Another comprehensive overview of methylphenidate can be found at drugbank.com.50
Matthijssen, Dietrich, Bierens, Kleine Deters, van de Loo-Neus, van den Hoofdakker, Buitelaar, Hoekstra (2019): Effects of Discontinuing Methylphenidate on Strengths and Difficulties, Quality of Life and Parenting Stress. J Child Adolesc Psychopharmacol. 2019 Dec 24. doi: 10.1089/cap.2019.0147. ↥
Matthijssen, Dietrich, Bierens, Kleine Deters, van de Loo-Neus, van den Hoofdakker, Buitelaar, Hoekstra (2019): Continued Benefits of Methylphenidate in ADHD After 2 Years in Clinical Practice: A Randomized Placebo-Controlled Discontinuation Study. Am J Psychiatry. 2019 Sep 1;176(9):754-762. doi: 10.1176/appi.ajp.2019.18111296. ↥
Castells, Ramon, Cunill, Olivé, Serrano (2020): Relationship Between Treatment Duration and Efficacy of Pharmacological Treatment for ADHD: A Meta-Analysis and Meta-Regression of 87 Randomized Controlled Clinical Trials. J Atten Disord. 2020 Feb 20:1087054720903372. doi: 10.1177/1087054720903372. PMID: 32075485. ↥
Parlatini V, Bellato A, Roy S, Murphy D, Cortese S (2024): Association Between Single-Dose and Longer Term Clinical Response to Stimulants in Attention-Deficit/Hyperactivity Disorder: A Systematic Review of Randomized Controlled Trials. J Child Adolesc Psychopharmacol. 2024 Jul 19. doi: 10.1089/cap.2024.0038. PMID: 39027968. ↥
Manza, Shokri-Kojori, Wiers, Kroll, Feldman, McPherson, Biesecker, Dennis, Johnson, Kelleher, Qu, Tomasi, Wang, Volkow (2021): Sex differences in methylphenidate-induced dopamine increases in ventral striatum. Mol Psychiatry. 2021 Oct 27. doi: 10.1038/s41380-021-01294-9. Epub ahead of print. PMID: 34707237. n = 95 ↥
Kooij, Bijlenga, Salerno, Jaeschke, Bitter, Balázs, Thome, Dom, Kasper, Filipe, Stes, Mohr, Leppämäki, Brugué, Bobes, Mccarthy, Richarte, Philipsen, Pehlivanidis, Niemela, Styr, Semerci, Bolea-Alamanac, Edvinsson, Baeyens, Wynchank, Sobanski, Philipsen, McNicholas, Caci, Mihailescu, Manor, Dobrescu, Krause, Fayyad, Ramos-Quiroga, Foeken, Rad, Adamou, Ohlmeier, Fitzgerald, Gill, Lensing, Mukaddes, Brudkiewicz, Gustafsson, Tania, Oswald, Carpentier, De Rossi, Delorme, Simoska, Pallanti, Young, Bejerot, Lehtonen, Kustow, Müller-Sedgwick, Hirvikoski, Pironti, Ginsberg, Félegeházy, Garcia-Portilla, Asherson (2018): Updated European Consensus Statement on diagnosis and treatment of adult ADHD, European Psychiatrie, European Psychiatry 56 (2019) 14–34, http://dx.doi.org/10.1016/j.eurpsy.2018.11.001, Seite 22, 7.4.1. ↥
Cortese, Adamo, Del Giovane, Mohr-Jensen, Hayes, Carucci, Atkinson, Tessari, Banaschewski, Coghill, Hollis, Simonoff, Zuddas, Barbui, Purgato, Steinhausen, Shokraneh, Xia, Cipriani (2018): Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: a systematic review and network meta-analysis. Lancet Psychiatry. 2018 Sep;5(9):727-738. doi: 10.1016/S2215-0366(18)30269-4. REVIEW ↥
Castello et al. 1992, zitiert nach Arnold: Journal of Attention Disorders Vol. 3(4):200-211 (2000) Methylphenidate vs. amphetamine: Comparative review. REVIEW ↥
LeBlond, Smith-Paine, Riemersma, Horn, Wade, Kurowski (2019): Influence of Methylphenidate on Long-Term Neuropsychological and Everyday Executive Functioning After Traumatic Brain Injury in Children with Secondary Attention Problems. J Int Neuropsychol Soc. 2019 Jun 10:1-10. doi: 10.1017/S1355617719000444. ↥
Handwerker (2007): Narkolepsie. Monatsschrift Kinderheilkunde. July 2007, Volume 155, Issue 7, pp 624–629 ↥
Peled, Cassuto, Berger (2019): Processing speed as a marker to stimulant effect in clinical sample of children with high functioning autism spectrum disorder. Nord J Psychiatry. 2019 Nov 5:1-5. doi: 10.1080/08039488.2019.1686063. ↥
Kooij, Bijlenga, Salerno, Jaeschke, Bitter, Balázs, Thome, Dom, Kasper, Filipe, Stes, Mohr, Leppämäki, Brugué, Bobes, Mccarthy, Richarte, Philipsen, Pehlivanidis, Niemela, Styr, Semerci, Bolea-Alamanac, Edvinsson, Baeyens, Wynchank, Sobanski, Philipsen, McNicholas, Caci, Mihailescu, Manor, Dobrescu, Krause, Fayyad, Ramos-Quiroga, Foeken, Rad, Adamou, Ohlmeier, Fitzgerald, Gill, Lensing, Mukaddes, Brudkiewicz, Gustafsson, Tania, Oswald, Carpentier, De Rossi, Delorme, Simoska, Pallanti, Young, Bejerot, Lehtonen, Kustow, Müller-Sedgwick, Hirvikoski, Pironti, Ginsberg, Félegeházy, Garcia-Portilla, Asherson (2018): Updated European Consensus Statement on diagnosis and treatment of adult ADHD, European Psychiatrie, European Psychiatry 56 (2019) 14–34, http://dx.doi.org/10.1016/j.eurpsy.2018.11.001, Seite 22, 7.4.4. ↥
Manni, Cipollone, Pallucchini, Maremmani, Perugi, Maremmani (2019): Remarkable Reduction of Cocaine Use in Dual Disorder (Adult Attention Deficit Hyperactive Disorder/Cocaine Use Disorder) Patients Treated with Medications for ADHD. Int J Environ Res Public Health. 2019 Oct 15;16(20). pii: E3911. doi: 10.3390/ijerph16203911. ↥
Crunelle, van den Brink, Schellekens, van de Glind, Icasa Consortium, Matthys (2019): [International consensus for the screening, diagnosis and treatment of adult patients with substance use disorder and ADHD]. [Article in Dutch] Tijdschr Psychiatr. 2019;61(7):477-487. ↥
Wilens, Faraone, Biederman, Gunawardene (2003): Does stimulant therapy of attention-deficit/hyperactivity disorder beget later substance abuse? A meta-analytic review of the literature; Pediatrics. 2003 Jan;111(1):179-85. REVIEW ↥
Edel, Vollmoeller (2006): Aufmerksamkeitsdefizit-/Hyperaktivitätsstörung bei Erwachsenen, Springer, Seite 120 ↥
Chang Z, Lichtenstein P, Halldner L, D’Onofrio B, Serlachius E, Fazel S, Långström N, Larsson H (2014): Stimulant ADHD medication and risk for substance abuse. J Child Psychol Psychiatry. 2014 Aug;55(8):878-85. doi: 10.1111/jcpp.12164. PMID: 25158998; PMCID: PMC4147667. ↥
Büchel, Peters, Banaschewski, Bokde, Bromberg, Conrod, Flor, Papadopoulos, Garavan, Gowland, Heinz, Walter, Ittermann, Mann, Martinot, Paillère-Martinot, Nees, Paus, Pausova, Poustka, Rietschel, Robbins, Smolka, Gallinat, Schumann, Knutson, the IMAGEN consortium (2012): Blunted ventral striatal responses to anticipated rewards foreshadow problematic drug use in novelty-seeking adolescents; Nat Commun. 2017; 8: 14140. doi: 10.1038/ncomms14140; PMCID: PMC5321762; n = 144 ↥
Lu, Chou, Hsiao, Hu, Yen (2019): Correlations of Internet Addiction Severity With Reinforcement Sensitivity and Frustration Intolerance in Adolescents With Attention-Deficit/Hyperactivity Disorder: The Moderating Effect of Medications. Front Psychiatry. 2019 Apr 26;10:268. doi: 10.3389/fpsyt.2019.00268. eCollection 2019. ↥
Zhang-James, Lloyd, James, Yang, Richards, Faraone (2019); Oral Methylphenidate Treatment of an Adolescent ADHD Rat Model Does Not Alter Cocaine-Conditioned Place Preference during Adulthood: A Negative Report. J Psychiatr Brain Sci. 2019;4. pii: e190021. doi: 10.20900/jpbs.20190021. ↥
Ide, Ikekubo, Hua, Takamatsu, Uhl, Sora, Ikeda (2018): Reward-enhancing effect of methylphenidate is abolished in dopamine transporter knockout mice: A model of attention-deficit/hyperactivity disorder. Neuropsychopharmacol Rep. 2018 Sep;38(3):149-153. doi: 10.1002/npr2.12020. ↥
Rösler, Retz (2020): Medikamentöse Therapie der ADHS bei Erwachsenen; Psychiatrie up2date 2020; 14: 59–75 ↥
Lastres-Becker I, Cebeira M, de Ceballos ML, Zeng BY, Jenner P, Ramos JA, Fernández-Ruiz JJ (2001): Increased cannabinoid CB1 receptor binding and activation of GTP-binding proteins in the basal ganglia of patients with Parkinson’s syndrome and of MPTP-treated marmosets. Eur J Neurosci. 2001 Dec;14(11):1827-32. doi: 10.1046/j.0953-816x.2001.01812.x. PMID: 11860478. ↥
Mailleux P, Vanderhaeghen JJ (1993): Dopaminergic regulation of cannabinoid receptor mRNA levels in the rat caudate-putamen: an in situ hybridization study. J Neurochem. 1993 Nov;61(5):1705-12. doi: 10.1111/j.1471-4159.1993.tb09807.x. PMID: 7901331. ↥
Romero J, Berrendero F, Pérez-Rosado A, Manzanares J, Rojo A, Fernández-Ruiz JJ, de Yebenes JG, Ramos JA (2000): Unilateral 6-hydroxydopamine lesions of nigrostriatal dopaminergic neurons increased CB1 receptor mRNA levels in the caudate-putamen. Life Sci. 2000;66(6):485-94. doi: 10.1016/s0024-3205(99)00618-9. PMID: 10794065. ↥
Elbe, Black, McGrane, Procyshyn (Hrsg.) (2019): Clinical Handbook of Psychotrophic Drugs for Children and Adolescents, 4th edition ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥
Patrick KS, Radke JL, Raymond JR, Koller L, Nguyen LV, Rodriguez W, Straughn AB (2019): Drug Regimen Individualization for Attention-Deficit/Hyperactivity Disorder: Guidance for Methylphenidate and Dexmethylphenidate Formulations. Pharmacotherapy. 2019 Jun;39(6):677-688. doi: 10.1002/phar.2190. PMID: 30351459. REVIEW ↥
https://www.kinderaerzte-im-netz.de/media/53ec94e833af614b730097d1/source/20080530092715_adhs2.pdf ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥
Banaschewski T, Coghill D, Santosh P, Zuddas A, Asherson P, Buitelaar J, Danckaerts M, Döpfner M, Faraone SV, Rothenberger A, Sergeant J, Steinhausen HC, Sonuga-Barke EJ, Taylor E (2006): Long-acting medications for the hyperkinetic disorders. A systematic review and European treatment guideline. Eur Child Adolesc Psychiatry. 2006 Dec;15(8):476-95. doi: 10.1007/s00787-006-0549-0. PMID: 16680409. REVIEW ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥ ↥
http://www.ads-hyperaktivitaet.de/FAQ/Infos/Medis/medis.html#1 ↥ ↥ ↥
Ryffel (2008): Vortrag beim Rheinfelder Herbstsymposium 6. November 2008 ↥
Ryffel (2003): Langzeiterfahrungen mit Stimulanzien bei ADHS: Empfehlungen für die Praxis. Forum der Kinder- und Jugendpsychiatrie und Psychotherapie, 13. J. Heft 1, S. 27 - 47, 2003 ↥
Goltz, Schröder (2021): Interaktionen mit PPI sind selten – aber es gibt Ausnahmen; Pharmazeutische Zeitung ↥ ↥
Yang X, Duan J, Fisher J (2016): Application of Physiologically Based Absorption Modeling to Characterize the Pharmacokinetic Profiles of Oral Extended Release Methylphenidate Products in Adults. PLoS One. 2016 Oct 10;11(10):e0164641. doi: 10.1371/journal.pone.0164641. PMID: 27723791; PMCID: PMC5056674. ↥
Childress AC, Marraffino A, Cutler AJ, Oh C, Brams MN (2023): Safety and Tolerability of Serdexmethylphenidate/Dexmethylphenidate Capsules in Children with Attention-Deficit/Hyperactivity Disorder: A 12-Month, Open-Label Safety Study. J Child Adolesc Psychopharmacol. 2023 Feb 20. doi: 10.1089/cap.2022.0076. PMID: 36809150. ↥
Medikamenten-Fachinformation des Herstellers ratiopharm ↥
Fachinformation Gelbe Liste Methylphenidathydrochlorid Hexal ↥
https://www.adhspedia.de/wiki/Datei:Methylphenidat-Spiegelverlauf.jpg ↥
https://www.uniklinik-ulm.de/fileadmin/default/Kliniken/Kinder-Jugendpsychiatrie/Praesentationen/Haege_2018_09_13_Curriculum_Potsdam.pdf, Seiten 17 und 18 ↥
Lenhart (2019): ADHS – Bei Erwachsenen häufig unterschätzt. Pharmazeutische Zeitung ↥
https://www.adhspedia.de/images/e/e7/Equasym-Kurve-Nahrung.jpg ↥
https://www.ratiopharm.de/assets/products/de/label/Methylphenidat-ratiopharm%20Hartkapseln%20mit%20veranderter%20Wirkstofffreisetzung%20-%2012.pdf?pzn=14281149, Seite 20 ↥
Novartis: Fachinformation Ritalin LA, unter 12.3. ↥
Gelbe Liste: Methylphenidat. Deutsch ↥
Schonwald, Chan, Nyp (2019): Not Really “The Same Thing”. J Dev Behav Pediatr. 2019 Dec 3. doi: 10.1097/DBP.0000000000000756. ↥
pharmgkb.org: Methylphenidate Pathway, Pharmacodynamics. Abruf 26.03.22 ↥
Drugbank: Methylphenidate. Abgerufen 30.03.2022 ↥